
 Alice Turing
Picture a student with a 3.8 GPA, strong references, and years of volunteer hours. She does everything a nursing program asks of her and still gets a rejection letter. The reason isn’t her grades. There simply isn’t a seat for her on a hospital unit.
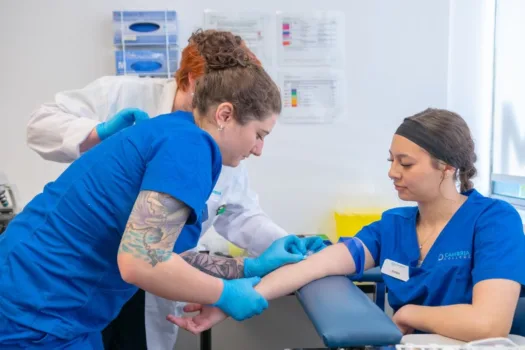
That story plays out thousands of times a year. The American Association of Colleges of Nursing (AACN) reports that interest in nursing is strong, yet schools can’t place everyone who qualifies. The bottleneck sits less in the classroom than on the hospital floor, where students have to log supervised clinical hours before they can graduate. Here’s why placements are the choke point, who it hurts most, and what programs can do about it.
Why Qualified Nursing Applicants Keep Getting Turned Away
Every nursing student needs a clinical site, a preceptor to supervise, and a faculty member to sign off. A program can only admit as many students as it can place. When one of those three runs short, the cohort shrinks, no matter how many strong applicants are waiting.
Consider a program coordinator juggling affiliation agreements, immunization records, and shift openings across a dozen hospitals. Each site has its own orientation rules and blackout dates, and every student’s paperwork expires on a different day. Many coordinators still manage this with email threads and spreadsheets, which is why programs are turning to clinical rotation software that keeps the schedule and the compliance records in one shared place. It won’t create new hospital seats, but it stops the seats a program already has from going to waste through double bookings and missed deadlines.
The scale of the gap is large. AACN’s 2025 survey found that 93,176 qualified applications were not accepted at US nursing schools. AACN is careful to note that this counts applications, not people, since one applicant may apply to several programs and enroll at another. Even so, the association names insufficient clinical placement sites, faculty, preceptors, and classroom space, along with budget cuts, as the primary barriers to admitting every qualified student.
What Makes Coordinating Clinical Rotations So Hard
Raw capacity is only half the story. Placements also have to match what students need to learn, and that’s where schedules fall apart.
Medical-surgical units tend to have room. Pediatric, psychiatric, and maternity placements are far scarcer, yet every student has to complete them. Our guide to nursing specializations shows how varied the field is, and each of those specialties needs its own training slots.
Then come the daily frictions. A preceptor cancels because of a staffing crunch. A hospital freezes student access during an accreditation visit. A vaccination record lapses two days before a rotation starts. Online and rural programs have it hardest, because students may live hours from the nearest partner hospital and have to travel to get their hours. Each hiccup pushes a student’s timeline back, and the delays pile up.
What This Means for Students, Including Those With Disabilities
For any student, an unpredictable placement schedule means uncertainty about childcare, jobs, housing, and graduation dates. A notice that arrives a week before a rotation, at a site an hour away, is a headache for most people. For a student with a chronic illness or a disability, it can be a barrier.
Someone who manages fatigue, plans medical appointments around a fixed routine, or needs an accessible site and an accommodation arranged in advance can’t easily absorb last-minute changes. The earlier a program locks in placements, the more time it has to confirm accommodations with the hospital rather than scramble once the semester has begun. That’s reasoning rather than a statistic, but it holds up. If that’s your situation, our tips for college applications with a disability or chronic illness cover how to raise accommodation needs early.
Predictability is an accessibility feature. Programs that publish placement timelines well ahead of each term make school workable for more people.
Practical Ways Programs Can Ease the Bottleneck
No single fix clears the backlog, but several steps help.
- Start planning earlier. Request placements for the next term while the current one is still running, and renew site agreements well before they expire.
- Build relationships with sites. Hospitals that see a program as organized and reliable tend to offer more slots over time.
- Centralize tracking. One schedule for every student, site, and document beats a pile of disconnected files.
- Use simulation as a supplement. The National Council of State Boards of Nursing (NCSBN) followed 666 graduates in its National Simulation Study and found no statistically significant differences in clinical competency, nursing knowledge, or NCLEX pass rates among students who replaced 25% or 50% of traditional clinical hours with simulation and those who didn’t.
That last point comes with a caveat: state boards of nursing set their own limits on how many clinical hours simulation can replace, so check your state’s rules first. Simulation also works best when it’s well designed and led by trained faculty. We covered how future clinicians are trained with these tools in our piece on preparing healthcare professionals for technology-driven care.
Why Capacity, Not Interest, Is the Constraint
It’s tempting to blame the shortage of nurses on a lack of young people who want the job. The data points the other way. AACN reports that enrollment in entry-level BSN programs rose 7.6% in 2025, adding 19,830 students for a total of 283,303. Demand is there. What’s missing is room to train everyone who’s ready.
That matters well beyond schools. Nurses do far more than staff a bedside; as we explored in our look at how nurses’ influence extends past the bedside, they shape care in clinics, communities, and policy. Every qualified applicant turned away is a future nurse patients never meet.
The Seats Are the Problem
Interest in nursing isn’t what’s holding the profession back. Seats and coordination are. Hospitals, regulators, and funders have to widen the pipeline, but programs control one piece of it right now: how well they use the placements they already have. Better scheduling won’t solve everything, yet it’s among the cheapest ways to open more space for students who are ready to start.

Follow me down the rabbit hole!
I'm Alice and I live with a dizzying assortment of invisible disabilities, including ADHD and fibromyalgia. I write to raise awareness and end the stigma surrounding mental and chronic illnesses of all kinds.




